





Eighty lakh doses, and twenty-two lakh of them in Uttar Pradesh alone. One hundred per cent of the identified target was covered in Gujarat, Uttar Pradesh, Madhya Pradesh and Mizoram. These are the figures the Union Ministry of Health and Family Welfare placed before the country on September 11, 2026, a little over six months after Prime Minister Narendra Modi launched the National HPV Vaccination Campaign from Ajmer on February 28. They deserve to be read slowly, because each unit in that total is a fourteen-year-old girl who will in all statistical likelihood, never develop the cancer that currently kills an Indian woman roughly every seven minutes.
More than eighty lakh doses of the Human Papillomavirus vaccine have been administered since February. The vaccine is offered free, as a single dose, to girls aged fourteen, at government health facilities and only after a parent or guardian has given informed consent. Registrar General of India projections for 2021 put the annual cohort of fourteen-year-olds at approximately 1.2 crore.
Delivery runs through Ayushman Arogya Mandirs, primary and community health centres, sub-district and district hospitals and government medical colleges. The ordinary capillaries of the public system rather than a parallel apparatus assembled for a photo opportunity.
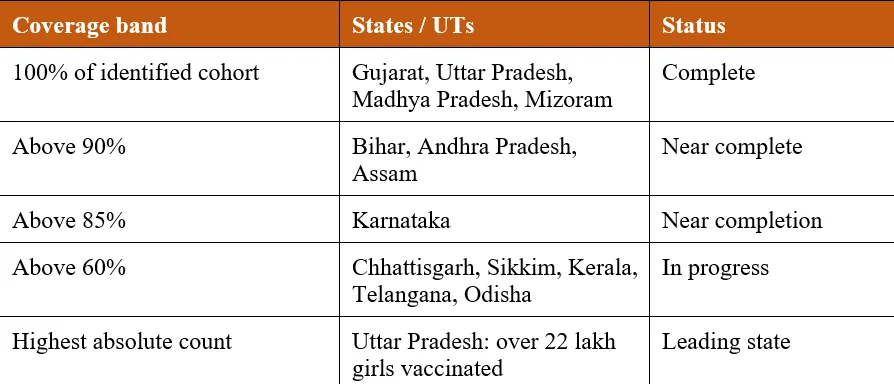
The state-level breakdown is where the achievement becomes legible. Gujarat, Uttar Pradesh, Madhya Pradesh and Mizoram have reached full coverage of their identified target populations. Bihar, Andhra Pradesh and Assam have crossed ninety per cent.
Karnataka has passed eighty-five. Chhattisgarh, Sikkim, Kerala, Telangana and Odisha have crossed sixty. Uttar Pradesh with more than twenty-two lakh adolescent girls vaccinated, has done the heaviest lifting in absolute terms, a state once treated as shorthand for administrative collapse now carrying the single largest share of a national preventive health drive.
A Wound that Never Healed Cleanly
To grasp why this is a political fact and not merely a logistical one, return to mid-2009. The Seattle-based organisation PATH, working with the Indian Council of Medical Research and the governments of Andhra Pradesh and Gujarat and funded by the Bill and Melinda Gates Foundation, ran what it called a demonstration project.
Roughly 23,000 girls between ten and fourteen received donated doses in Khammam and Vadodara. Seven girls died. The Health Ministry suspended the project in 2010 and the 72nd Parliamentary Standing Committee on Health and Family Welfare tabled a scathing report in the Rajya Sabha on 30 August 2013, concluding that a clinical trial had been conducted under the softer label of observation, with consent procedures that could not withstand scrutiny.
Honesty requires two things to be said together. No causal link was ever established between the vaccine and those seven deaths, the reported causes were unrelated. But the regulatory conduct was indefensible and the Ministry’s own 2014 response to Parliament conceded collective failure three times over. India then did what institutions do when they are embarrassed it went quiet.
The silence lasted sixteen years and a legitimate grievance about research ethics curdled in that vacuum, into a general belief that the vaccine itself was the danger. Jagat Prakash Nadda, who sat on the committee that delivered the 2013 indictment and who now presides over the Ministry running the national rollout is a fair emblem of the distance travelled.
Starting of the Rumors
What blunted the rumour here was not a counter-campaign on the same platforms, though radio, posters and digital outreach were all duly deployed. It was that the person asking a mother for consent was usually a frontline health worker she already knew, standing in a health centre she had used before.
Misinformation travels through screens, trust travels through faces. India’s frontline network, built over decades and mobilised here through district-level health teams, remains its most underrated and least celebrated line of defence against an infodemic.
On 26 February, two days before the launch, the gynaecologist who posts as @PoornimaNimo published a widely shared rebuttal pointing out that India records about 1,27,526 new cervical cancer cases a year and that the three HPV vaccines in Indian uses Cervavac from the Serum Institute, Gardasil from Merck and Cervarix from GSK which are owned by none of the philanthropists named in the conspiracy.
Fake News.
📌India reports about 127,526 new cases of cervical cancer annually.
📌Giving the HPV vaccine to young girls is a way to prevent cancer decades before it could develop.
📌HPV (Human Papillomavirus) is a very common virus spread through skin-to-skin contact.
📌HPV… pic.twitter.com/LMatwUoSlj— Dr Poornima 🇮🇳 (@PoornimaNimo) February 26, 2026
The Mumbai surgeon @amitsurg, posting on 25 February, set the efficacy range at 93 to 100 per cent against the targeted HPV types and noted that litigation against the vaccine had largely collapsed in foreign courts.
The vaccine is fine, all cases against it have pretty much been thrown out by the court and lawyers are now reduced to pleading that recipients weren’t informed that they could feel briefly giddy after the shot. And maybe you should have read the link properly before posting. 🙂 https://t.co/0kFnGqjdJ2 pic.twitter.com/O9aljxdtzq
— Amit Thadhani (@amitsurg) February 25, 2026
The peer-reviewed content analysis of HPV conversation on X has found that close to a quarter of posts on the subject carry misinformation, and that those posts attract higher engagement than accurate ones.
A geospatial sentiment study of Indian HPV tweets, published in Global Public Health, extracted 1,487 posts and analysed 1,010 of them, finding overall positive sentiment coexisting with a persistent seam of safety and ethics misinformation.
In August 2026, researchers at the Central University of Punjab published a commentary in Human Vaccines & Immunotherapeutics arguing that the campaign’s success rate would fall sharply unless hesitancy and misinformation were addressed as a communication problem in their own right.

When the Influencer Became the Petitioner
The Indian version of vaccine scepticism has a distinctive feature, it did not stay on the timeline. The public interest litigation heard by the Delhi High Court on 29 July was filed by the gynaecologist Dr Sujata Mittal along with Jitendra Chouksey, the fitness entrepreneur behind the FITTR platform (Dr. Sujata Mittal & Anr v. Union of India and Others) who had already told a large social media following that he was disinclined to recommend the vaccine to his own family.
Their plea questioned the data, the efficacy and the necessity of the programme, argued that school-based sessions and enrolment targets for ASHA workers amounted to pressure on young girls, and cited a fourteen-year-old from Tamil Nadu said to have developed severe neurological symptoms after vaccination in March 2026.
That is the modern pipeline in full of a claim which is made to an audience of millions, the audience treats reach as credentials, and the claim is then carried into a constitutional court as a grievance requiring judicial remedy. Nothing about it is illegal. Everything about it is a test of whether the state can answer speed with evidence.
When Supreme Courts enter
A bench of Chief Justice Devendra Kumar Upadhyaya and Justice Tejas Karia declined to stay the drive, recording the government’s submission that of roughly fifty-five lakh doses administered by then, about 120 recipients had reported nothing worse than nausea or headache.
The court did not hand the Centre a clean chit and it insisted that protocol be followed, sought affidavits from the Centre, ICMR, CDSCO and the National Immunization Technical Advisory Group, and listed the matter for 29 October. But it refused to halt a preventive programme on the strength of contested anecdote.
Six weeks later the Supreme Court was blunter. On 10 September, a bench of Chief Justice of India Surya Kant with Justices Joymalya Bagchi and V Mohana heard a petition from the Universal Health Organisation which, while disclaiming any anti-vaccine intent, again raised the fertility claim alongside demands on adverse-event monitoring and injury compensation.
The bench signalled at the outset that it would not entertain the matter, warned that a public health programme should not be derailed by assertions unsupported by adequate research and indicated it would record strong observations if the plea were pressed later the petitioner withdrew.
The Rumour Countered by Experts
The campaign was launched into hostile weather. Within hours of the Ajmer event, social media carried the familiar catalogue that the vaccine causes infertility, that it triggers neurological and autoimmune disease, that it encourages early sexual activity, that it is a foreign philanthropist experiment on Indian daughters.
Dr Abhishek Shankar of AIIMS Delhi has described these claims as driven by viral, unverified anecdote rather than evidence, and has warned that the consequence is not confined to argument online. Hesitancy shows up in clinics as missed appointments, delayed vaccination, and preventable cancers arriving late.
At a free vaccination camp organised during a government expo at Bharat Mandapam in July, only thirty-four of two hundred eligible girls accepted the shot. Doctors there reported that roughly every second parent asked whether the vaccine would affect their daughter’s future fertility. This is worth dwelling on, because it dismantles a lazy assumption. Resistance is not a rural or an illiterate phenomenon. It flourishes in Delhi, among parents with smartphones and opinions.
In Pakistan first HPV campaign, launched in September 2025, aimed at eleven million girls and finished with roughly half that number vaccinated. Health workers had doors shut on them, schools closed for days, families concealed their daughters ages and a prominent political-religious figure told a Karachi rally that the nation’s daughters were being made infertile.
The difference between that outcome and India’s eighty lakh is not a difference in the quality of the rumour. It is a difference in the quality of the state that met it.
What the Programme Does About Fear
The design of the Indian campaign is itself an argument, and a quietly sophisticated one. Vaccination is voluntary, which answers the coercion charge. Parental consent is mandatory, which answers the charge that the state is acting over the heads of families. Every session is conducted under the supervision of a trained medical officer.
Every site is linked to a round-the-clock facility for the assessment and management of rare Adverse Events Following Immunisation, which answers, structurally rather than the memory of 2009. The programme did not ask the country to forget the last time; it built the safeguards whose absence caused the last time.
There is also the weight of global evidence. More than 500 million HPV vaccine doses have been administered worldwide since 2006, making these among the most extensively studied vaccines in existence.
India has joined over 160 countries that include HPV vaccination in their national immunisation schedules, and more than ninety are using the single-dose regimen that improves coverage, affordability and programme efficiency in one stroke.
The Company India Now Keeps
The case for urgency rests on a figure that ought to be better known. According to GLOBOCAN 2022 data cited by the government, cervical cancer is the second most common cancer among Indian women, with more than 1.2 lakh new cases and close to 80,000 deaths annually than the highest death toll of any country and almost a quarter of the world’s total.
Persistent infection with high-risk HPV types, chiefly 16 and 18, accounts for nearly all of it. A new case is diagnosed roughly every four minutes. Globally, 87 per cent of upper-middle-income countries, 78 per cent of lower-middle-income countries and 54 per cent of low-income countries have adopted HPV vaccination in their national programmes.
India the world’s largest vaccine producer, supplying close to sixty per cent of global vaccine volumes, was for sixteen years absent from that list. That anomaly has now closed. Eighty lakh doses against an annual cohort of about 1.2 crore means roughly a third of this year’s eligible girls are still waiting.
The Ministry release names the achievers which is understandable as communication and unhelpful as accountability. States that have not crossed sixty per cent deserve to be identified, because sunlight has historically done more for immunisation coverage in India than exhortation.
The campaign is entering its final phase and the last mile is always the steepest. The remaining gap is likely to be concentrated in two very different places where out-of-school girls in districts with weak frontline penetration and well-off urban households that have decided, on the strength of a forwarded video, that they know better. These require opposite instruments more health workers for the first, more credible doctors speaking in regional languages for the second.
Swastha Nari and the concept of Antoydaya in Action
Charaka defined the purpose of medicine as the preservation of health in the healthy before the alleviation of disease in the sick. By that standard, a single free dose given to a fourteen-year-old in a Dindori hamlet or a Mizoram village, identical to the one a private clinic in South Delhi charges for is not merely a health intervention. It is Antyodaya rendered in a syringe: the last girl first, protected decades before the risk arrives by a system that no longer asks what her family can pay.
The misinformation has not stopped and will not. But eighty lakh Indian families have now weighed a rumour against a doctor and chosen the doctor. That delivery without compulsion and repeated eight million times is the most persuasive public health argument India has made in a decade.









